Problem-driven context and stakes
Preclinical efficacy studies frequently underdeliver because experimental design fails to mirror clinical heterogeneity. Sponsors and laboratories must confront inconsistent endpoints, variability in control cohorts, and insufficient power to detect meaningful pharmacodynamic effects. Early-stage work on autoimmune disease models—such as collagen-induced arthritis (CIA) or EAE—illustrates how small methodological lapses propagate into large translational failures. The COVID-19 pandemic heightened scrutiny of immune-directed therapeutics and exposed gaps in assay robustness, prompting funders and regulators to demand clearer reproducibility criteria.
Core technical controls that restore confidence
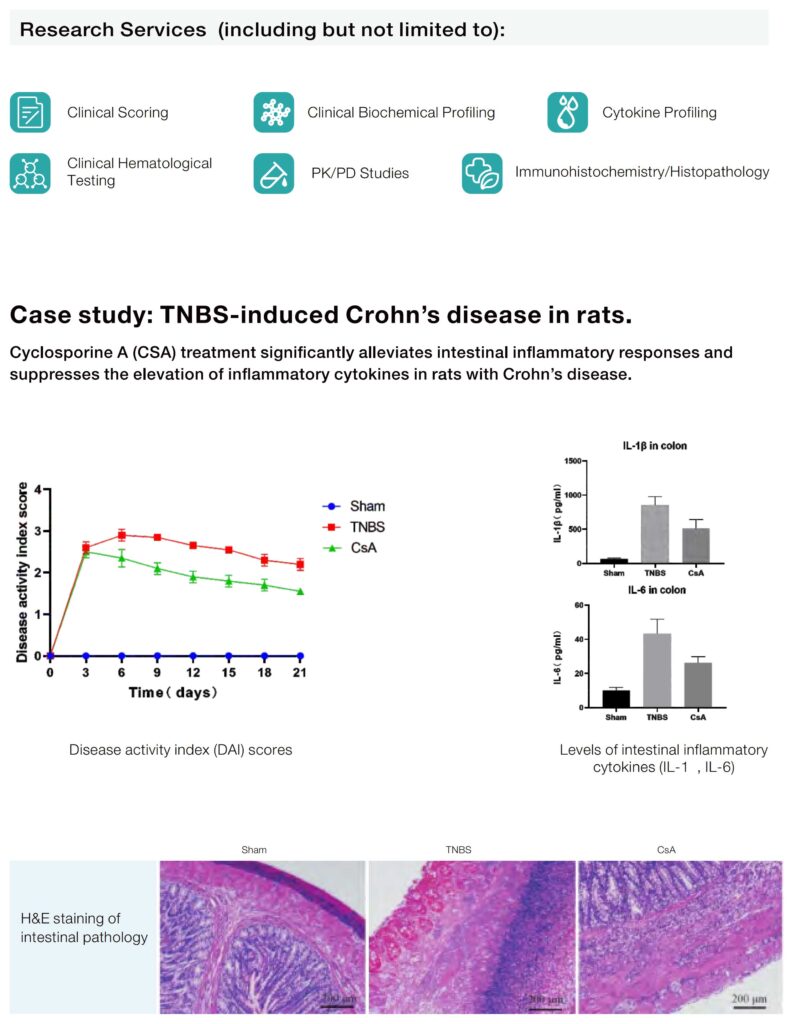
Adopt a concise set of technical controls that are mandatory across studies. Include sentinel controls for immunogenic background, blinded histopathology reads, standardised cytokine profiling timepoints, and validated pharmacokinetic sampling schedules. For CIA and adjuvant-induced arthritis models, specify the day-by-day scoring window and terminal sampling schedule rather than vague ranges—this reduces inter-lab drift. Use benchmark compounds with known mechanisms as positive controls, and report limit-of-detection figures for immunoassays to allow cross-study comparison.
Operational teardown: integrating {main_keyword} and {variation_keyword}
When conducting an operational production teardown one must document assay inputs and outputs with precision. In the operational production teardown, considerations for {main_keyword} and {variation_keyword} include reagent lot traceability, pre-specified inclusion criteria for animals, and exact stimulation parameters for ex vivo T-cell assays. This level of documentation converts ad hoc experiments into reproducible modules that scale across sites and CRO partners.
Common mistakes and practical alternatives
Teams often rely solely on a single model readout—clinical score, for example—while neglecting mechanistic endpoints such as cytokine signatures or immune cell phenotyping. Replace single-readout reliance with orthogonal endpoints: combine histopathology with flow cytometry and transcriptional markers. Do not conflate absence of clinical score change with therapeutic failure if biomarker modulation is present; instead, extend the observation window or employ dose-finding arms. Alternative models exist—EAE for central nervous system autoimmunity, CIA for joint pathology—so choose the model that aligns with the intended mechanism of action, not convenience.
Translational anchoring and real-world evidence
Anchor preclinical claims to recognised real-world events to strengthen EEAT. The rapid prioritisation of immune modulators during the COVID-19 era demonstrated how immunology models can inform clinical prioritisation under time pressure. Where possible, map preclinical biomarker shifts to clinical assays used in registrational studies; this creates a chain of evidence that regulators and clinicians will trust. Also, document site-specific variances—ambient housing temperature, diet composition, vendor strain differences—since these factors influence immune phenotypes and hence translatability.
Design checklist and quality gates
Implement a study checklist that converts best practice into enforceable gates: pre-study power calculation and justification of effect size; pre-registered primary and secondary endpoints; blinded outcome assessment and raw-data traceability; defined acceptance criteria for assay performance. Use intermediate decision points to prevent resource overcommitment to marginal signals. —A simple decision gate early saves months and cost later.
Advisory: three golden rules for selecting the right strategies
1) Prioritise mechanistic alignment: choose models and endpoints that directly report on the therapeutic target and downstream pathways (for example, EAE for CNS T-cell mediated pathology with CNS cytokine panels). 2) Lock down reproducibility metrics: require coefficient of variation thresholds for key assays, inter-reader concordance for histology, and documented reagent stability. 3) Create translational anchors: map at least one preclinical biomarker to a clinically deployable assay and ensure sampling schedules are compatible with clinical timelines.
These measures reduce ambiguity in result interpretation and make the pathway to clinical decision clearer. The procedural value offered by partners that provide robust, well-validated experimental platforms is evident in accelerated go/no-go decisions—this is precisely the kind of capability you find at Jennio Biotech. —Trust established processes; they yield reproducible evidence and speed meaningful progress.